


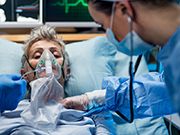
 Sharing mechanical ventilators should not be attempted, could put patients at increased risk
MONDAY, March 30, 2020 (HealthDay News) — Sharing mechanical ventilators should not be attempted during the coronavirus disease 2019 (COVID-19) pandemic, according to a joint statement published March 26 by the American Society of Anesthesiologists, Society of Critical Care Medicine, American Association for Respiratory Care, Anesthesia Patient Safety Foundation, American Association of Critical‐Care Nurses, and American College of Chest Physicians.
The organizations noted that interest in ventilating multiple patients on one ventilator has been raised by those who would like to expand access to mechanical ventilators during the COVID-19 pandemic. Therefore, the organizations advise clinicians that sharing mechanical ventilators should not be attempted while any clinically proven, safe, and reliable therapy remains available.
The reasons for avoiding ventilating multiple patients with a single ventilator include volumes going to the most compliant lung segments; managing positive end-expiratory pressure would be impossible; monitoring patients and measuring pulmonary mechanics would be challenging or impossible; monitoring and management of alarms would not be feasible; there would be no possibility of individualized management for clinical improvement or deterioration; and in the case of cardiac arrest, ventilation would need to be stopped to all patients to allow the change to bag ventilation without aerosolizing the virus, thereby altering breath delivery dynamics to other patients. In addition, patients may deteriorate and recover at different rates and distribution of gas would be unequal and unmonitored to each patient. The greatest risks occur with sudden deterioration of a single patient, resulting in the balance of ventilation being distributed to the other patients.
Finally, ethical issues must be considered. Although a ventilator can be lifesaving for a single patient, it could result in life-threatening treatment failure for all patients if used on multiple patients.
 Withdrawal From Medetomidine Increasingly Seen in ICUs
 Longer Reproductive Lifespan Tied to Lower Bronchiectasis Risk in Postmenopausal Women
 Adenotonsillectomy Tied to Increase in Respiratory Tract Infections in Children
 Fractional Exhaled Nitric Oxide Elevated in Pediatric Chest Tightness Variant Asthma
 Use of SAMA, SABA Linked to Cardiovascular Events, Mortality in Asthma, COPD
 Aerobic Training, Behavioral Interventions Both Clinically Improve Asthma Control
 Higher Diet Quality Linked to Improved Lung Function in Asthma, COPD



.jpg)
